
上海交通大学学报(医学版) ›› 2026, Vol. 46 ›› Issue (9): 1299-1306.doi: 10.3969/j.issn.1674-8115.2026.09.015
• 综述 • 上一篇
范逸尘1, 庄若曦1, 邱朝晖2, 韩丹3( ), 李岩1()
收稿日期:2025-11-19
接受日期:2026-05-08
出版日期:2026-09-21
发布日期:2026-09-21
通讯作者:
李 岩,教授,博士;电子信箱:ly316@126.com。作者简介:第一联系人:为共同通信作者。
Fan Yichen1, Zhuang Ruoxi1, Qiu Zhaohui2, Han Dan3(), Li Yan1()
Received:2025-11-19
Accepted:2026-05-08
Online:2026-09-21
Published:2026-09-21
Contact:
Li Yan, E-mail: ly316@126.com.摘要:
心血管植入式电子装置(cardiovascular implantable electronic device,CIED)是心律失常相关疾病重要的治疗和预防手段,目前其相关技术发展迅速。CIED植入在临床上可选择的常用入路包括锁骨下静脉、头静脉和腋静脉。该类手术入路的选择需综合评估静脉解剖特征、穿刺操作难度及装置远期使用的安全性与有效性。临床应用中,术者尤其需关注静脉入路的选择及其与穿刺成功率、可能并发症的关联。此外,X线、超声等影像学引导技术的应用有利于术者掌握静脉走行与毗邻结构,降低穿刺相关并发症风险,进一步提升手术成功率。该文结合静脉的解剖学特征与临床操作经验,总结了3种静脉的常见变异与相关风险,以及影像学引导的新技术,从而为临床心血管电子装置植入术提供解剖学参考。
中图分类号:
范逸尘, 庄若曦, 邱朝晖, 韩丹, 李岩. 心血管电子装置植入术中静脉入路选择的解剖学比较[J]. 上海交通大学学报(医学版), 2026, 46(9): 1299-1306.
Fan Yichen, Zhuang Ruoxi, Qiu Zhaohui, Han Dan, Li Yan. Anatomical comparison of venous access options during cardiovascular electronic device implantation[J]. Journal of Shanghai Jiao Tong University (Medical Science), 2026,(9): 1299-1306.
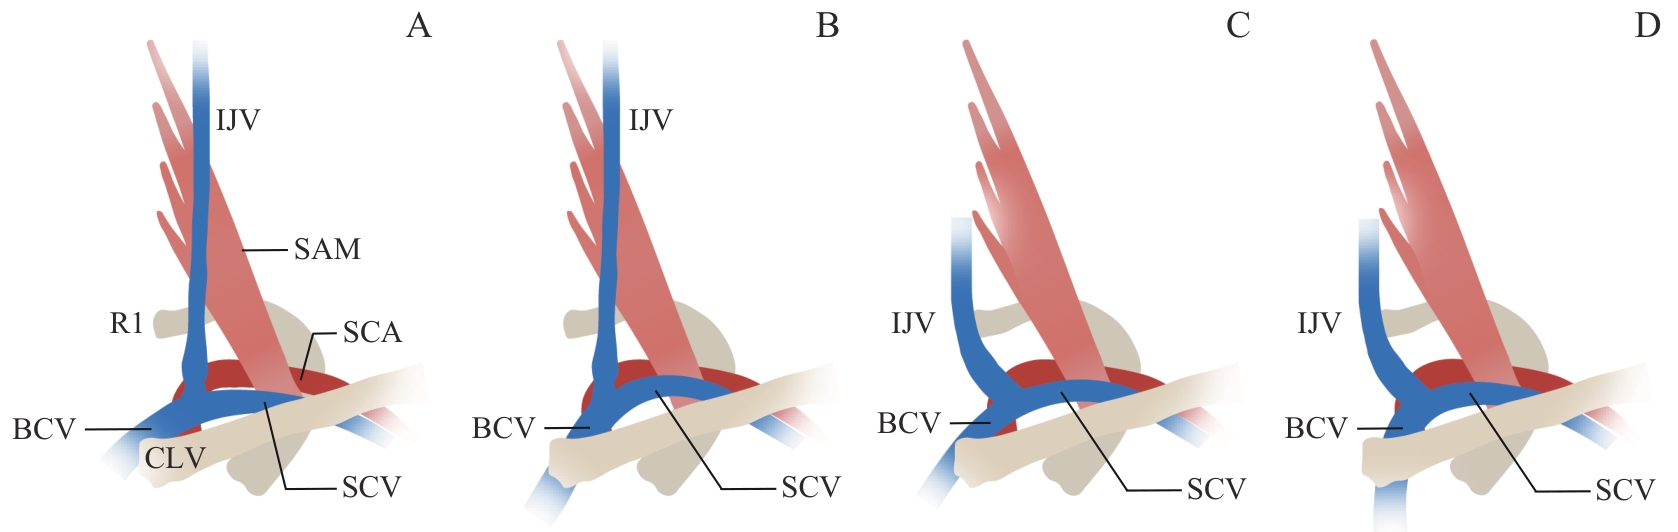
图1 锁骨下静脉分型示意图Note: A. Type Ⅰ. B. Type Ⅱ. C. Type Ⅲ. D. Type Ⅳ. IJV—internal jugular vein; R1—first rib; BCV—brachiocephalic vein; CLV—clavicle; SCV—subclavian vein; SCA—subclavian artery; SAM—anterior scalene muscle.
Fig 1 Schematic diagram of the classification of the subclavian vein
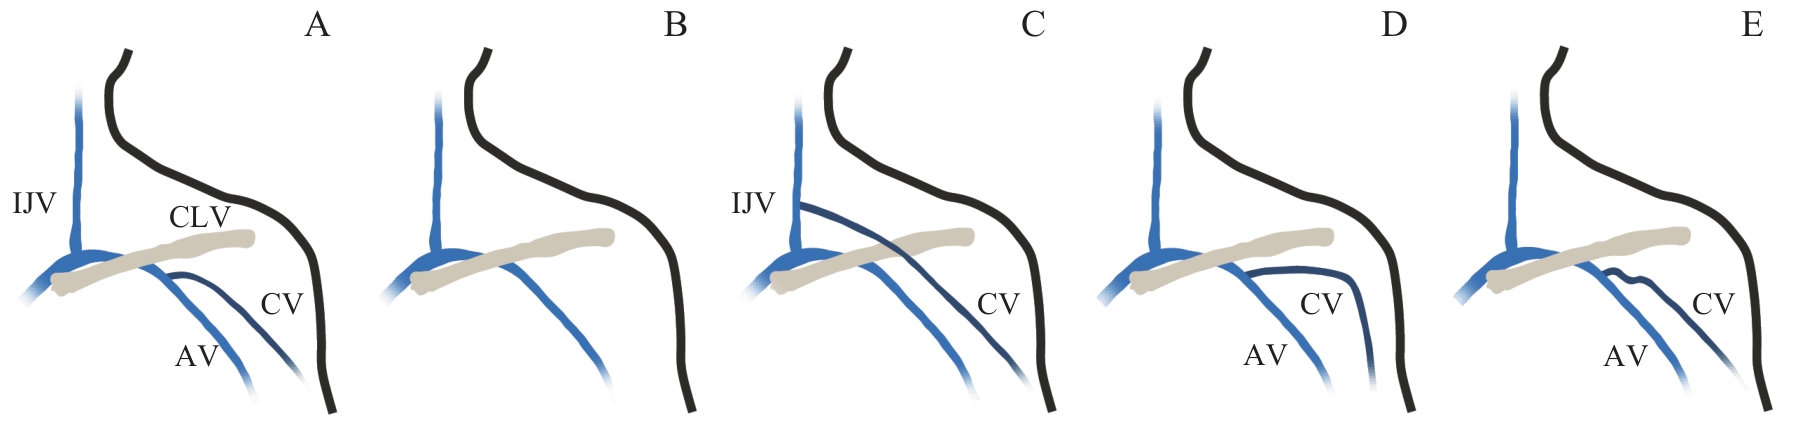
图2 头静脉变异示意图Note: A. Standard course. B. Absence of the cephalic vein. C. Cephalic vein drains into the internal jugular vein. D. Cephalic vein runs lateral to the deltoid-pectoralis groove. E. Cephalic vein is tortuous. AV—axillary vein; CV—cephalic vein.
Fig 2 Schematic diagram of the variations of the cephalic vein
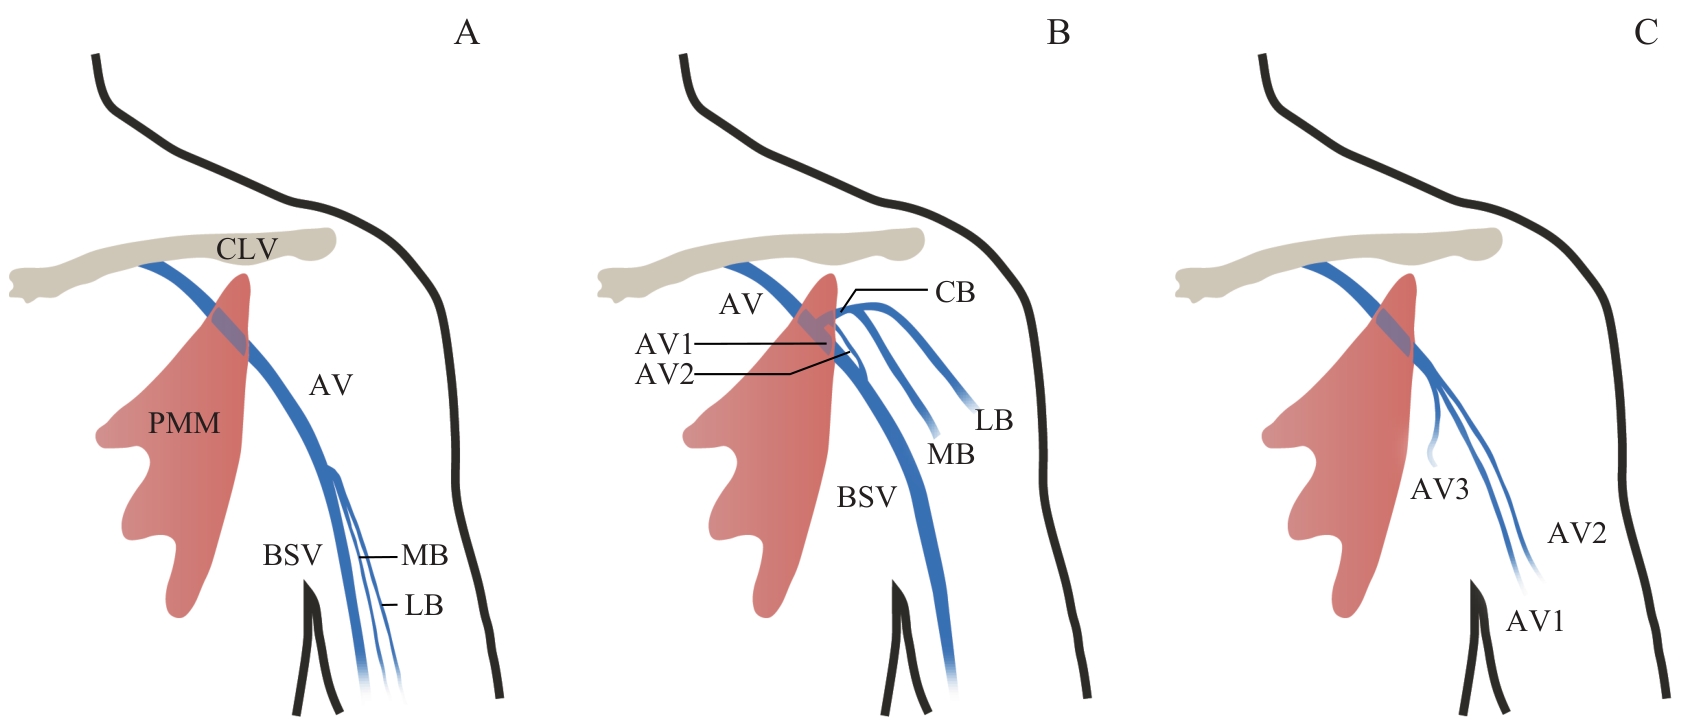
图3 腋静脉变异示意图Note: A. Normal axillary vein. B. Two-branch variant. C. Three-branch variant. PMM—pectoralis minor muscle; BSV—basilic vein; MB—medial brachial vein; LB—lateral brachial vein; CB—common brachial vein.
Fig 3 Schematic diagram of variations of the axillary vein
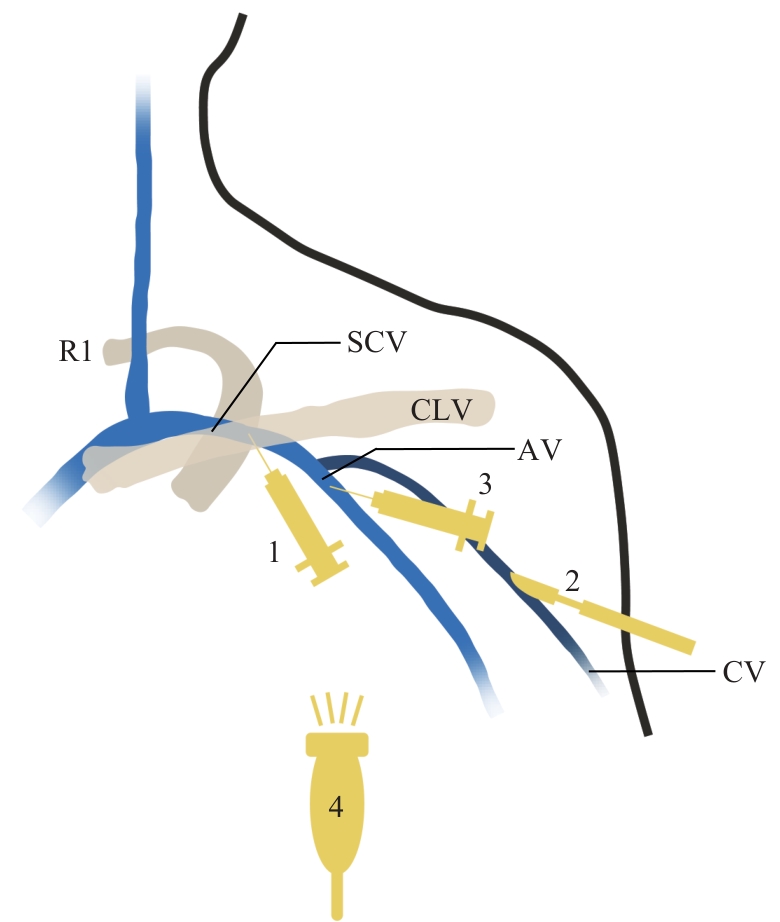
图4 SVP、CVC及足侧透视下AVP的示意图Note: 1—SVP, insert the needle at an angle toward the supraclavicular fossa at the junction of the clavicle and the first rib to complete the puncture; 2—CVC, make a skin incision in the deltoid-pectoralis major groove, expose the cephalic vein, and perform a venotomy; 3—AVP, direct the needle toward the sternoclavicular joint and perform the puncture in the third segment of the axillary vein, located between the upper border of the pectoralis minor muscle and the lower border of the clavicle; 4—caudal fluoroscopy, this fluoroscopic angle enhances the safety of the puncture procedure.
Fig 4 Schematic diagram of SVP, CVC, and AVP under caudal fluoroscopy
| Parameter | SVP | CVC | AVP | |
|---|---|---|---|---|
| X-ray fluoroscopy | Ultrasound guidance | |||
| Surface landmark | Junction of the clavicle and R1 | Deltoid-pectoralis groove | No distinct surface landmark, difficult to localize | |
| Depth | Deep; penetration of the subclavius muscle and fascia required | Superficial, course within the subcutaneous superficial fascia | Moderate, located beneath the deep fascia | |
| Diameter | Large, suitable for multiple-lead implantation | Small | Large, suitable for multiple-lead implantation | |
| Anatomical variation | Rare | Frequent | Frequent | |
| Trajectory | Straight, easy lead advancement to the heart | Tortuous, via the cephalic-subclavian vein angle | Straight, similar to the subclavian vein | |
| Adjacent structure | ||||
| Artery and nerve | Adjacent to the subclavian artery and brachial plexus; puncture errors frequently observed | No major vessels or nerves in proximity | Adjacent to the axillary artery and brachial plexus | |
| Pleura | Extremely close | Distant | Distant | |
| Passage through costoclavicular space | Yes | No | No | |
| Procedural difficulty | Moderate | Simple; surgical training required | Relatively high | Moderate; ultrasound equipment training required |
| Success rate | High (>95%) | Lower (~80%) | High (>95%) | |
| Procedure time | Short | Longer, cephalic vein cutdown required | Moderate | Short, reduced number of attempts |
| Complication risk | ||||
| Pneumothorax | High | No risk | Low | |
| Subclavian crush syndrome | High | Very low | Low | |
| Others | Risk of inadvertent arterial puncture, thoracic duct injury, and brachial plexus injury | Low risk of inadvertent puncture, risks of phlebitis and thrombosis | Risk of inadvertent arterial puncture and brachial plexus injury | Very low risk of inadvertent puncture |
| Risk related to imaging | ||||
| Radiation exposure | ‒ | ‒ | High | Low |
| Iodinated contrast medium | ‒ | ‒ | Required; potential nephrotoxicity | Not required |
表1 不同静脉入路的解剖学特征、手术成功率与风险比较
Tab 1 Anatomical characteristics, success rates, and risks of different venous access routes
| Parameter | SVP | CVC | AVP | |
|---|---|---|---|---|
| X-ray fluoroscopy | Ultrasound guidance | |||
| Surface landmark | Junction of the clavicle and R1 | Deltoid-pectoralis groove | No distinct surface landmark, difficult to localize | |
| Depth | Deep; penetration of the subclavius muscle and fascia required | Superficial, course within the subcutaneous superficial fascia | Moderate, located beneath the deep fascia | |
| Diameter | Large, suitable for multiple-lead implantation | Small | Large, suitable for multiple-lead implantation | |
| Anatomical variation | Rare | Frequent | Frequent | |
| Trajectory | Straight, easy lead advancement to the heart | Tortuous, via the cephalic-subclavian vein angle | Straight, similar to the subclavian vein | |
| Adjacent structure | ||||
| Artery and nerve | Adjacent to the subclavian artery and brachial plexus; puncture errors frequently observed | No major vessels or nerves in proximity | Adjacent to the axillary artery and brachial plexus | |
| Pleura | Extremely close | Distant | Distant | |
| Passage through costoclavicular space | Yes | No | No | |
| Procedural difficulty | Moderate | Simple; surgical training required | Relatively high | Moderate; ultrasound equipment training required |
| Success rate | High (>95%) | Lower (~80%) | High (>95%) | |
| Procedure time | Short | Longer, cephalic vein cutdown required | Moderate | Short, reduced number of attempts |
| Complication risk | ||||
| Pneumothorax | High | No risk | Low | |
| Subclavian crush syndrome | High | Very low | Low | |
| Others | Risk of inadvertent arterial puncture, thoracic duct injury, and brachial plexus injury | Low risk of inadvertent puncture, risks of phlebitis and thrombosis | Risk of inadvertent arterial puncture and brachial plexus injury | Very low risk of inadvertent puncture |
| Risk related to imaging | ||||
| Radiation exposure | ‒ | ‒ | High | Low |
| Iodinated contrast medium | ‒ | ‒ | Required; potential nephrotoxicity | Not required |
| [1] | 中华医学会心电生理和起搏分会, 中国医师协会心律学专业委员会. 心血管植入型电子器械术后随访的专家共识(2020)[J]. 中华心律失常学杂志, 2020, 24(6): 532-544. |
| Chinese Society of Pacing and Electrophysiology, Chinese Society of Arrhythmias. Expert consensus on the follow-up of cardiovascular implantable electronic devices (2020)[J].Chinese Journal of Cardiac Arrhythmias, 2020, 24(6): 532-544. | |
| [2] | 黄嘉慧, 沈红, 赵云玲, 等. 植入CIED患者选择社区随访的影响因素及其效果初探[J]. 中华全科医师杂志, 2023, 22(2): 187-193. |
| Huang J H, Shen H, Zhao Y L, et al. Influencing factors and effectiveness of community follow-up in patients with cardiac implantable electronic device[J]. Chinese Journal of General Practitioners, 2023, 22(2): 187-193. | |
| [3] | Brignole M, Deharo J C. Different techniques of venous access for CIEDs: advantages and disadvantages[J]. Eur Heart J, 2023, 44(46): 4859-4861. |
| [4] | 徐志宾, 徐远, 王鑫. 颈静脉、锁骨下静脉汇入无名静脉区的影像解剖分型研究及其在中心静脉置管中的应用[J]. 海南医学, 2024, 35(2): 258-261. |
| Xu Z B, Xu Y, Wang X. Study on imaging anatomy classification of jugular vein and subclavian vein into innominate vein area and its application in central venous catheterization[J]. Hainan Medical Journal, 2024, 35(2): 258-261. | |
| [5] | 中华医学会心电生理和起搏分会, 中国医师协会心律学专业委员会. 普通心脏起搏器和植入型心律转复除颤器手术操作规范中国专家共识(2023)[J]. 中华心脏与心律电子杂志, 2023, 11(2): 65-102. |
| Chinese Society of Pacing and Electrophysiology, Chinese Society of Arrhythmias. Chinese expert consensus and practical guide on optimal implantation technique for conventional pacemakers and implantable cardioverter defibrillators (2023)[J]. Chinese Journal of Heart and Heart Rhythm, 2023, 11(2): 65-102. | |
| [6] | Su J L, Kusumoto F M, Zhou X, et al. How to perform extrathoracic venous access for cardiac implantable electronic device placement: detailed description of techniques[J]. Heart Rhythm, 2022, 19(7): 1184-1191. |
| [7] | Burri H, Starck C, Auricchio A, et al. EHRA expert consensus statement and practical guide on optimal implantation technique for conventional pacemakers and implantable cardioverter-defibrillators: endorsed by the Heart Rhythm Society (HRS), the Asia Pacific Heart Rhythm Society (APHRS), and the Latin-American Heart Rhythm Society (LAHRS)[J]. Europace, 2021, 23(7): 983-1008. |
| [8] | Zhu J G, Sun L, Ruan Z B. Improved axillary vein puncture in implantation of pacemaker electrode leads[J]. Asian J Surg, 2022, 45(6): 1263-1264. |
| [9] | 杨玲玉, 丁鹏飞, 陈剑楠, 等. 头静脉分型及头静脉法置入起搏电极的临床研究[J]. 中国心脏起搏与心电生理杂志, 2023, 37(4): 294-298. |
| Yang L Y, Ding P F, Chen J N, et al. Classification of cephalic vein and clinical study of cephalic vein pacing electrode implantation[J]. Chinese Journal of Cardiac Pacing and Electrophysiology, 2023, 37(4): 294-298. | |
| [10] | Won H S, Shin J O, Nam S M, et al. Supraclavicular cephalic vein draining into the internal jugular vein via the external jugular vein[J]. Surg Radiol Anat, 2023, 45(4): 487-490. |
| [11] | Li B X, Yang Z C, Wang X, et al. A variation in the course of the cephalic vein merging into basilic vein into axillary vein: a case report[J]. Asian J Surg, 2023, 46(4): 1888-1889. |
| [12] | 杨玲玉, 李学文. 经头静脉植入心血管植入型电子器械的方法[J]. 局解手术学杂志, 2023, 32(7): 641-644. |
| Yang L Y, Li X W. Methods for implantation of cardiovascular implantable electronic devices via cephalic vein[J]. Journal of Regional Anatomy and Operative Surgery, 2023, 32(7): 641-644. | |
| [13] | Zhang W B, Pang J, Zhou Y. Delayed development of a huge chest wall hematoma post pacemaker implantation: a case report[J]. Pacing Clin Electrophysiol, 2024, 47(4): 564-567. |
| [14] | 张朝佑. 人体解剖学[M]. 3版. 北京: 人民卫生出版社, 2009: 889. |
| Zhang C Y. Human anatomy [M]. 3rd ed. Beijing: People′s Medical Publishing House, 2009: 889. | |
| [15] | Yang H J, Gil Y C, Jin J D, et al. Novel findings of the anatomy and variations of the axillary vein and its tributaries[J]. Clin Anat, 2012, 25(7): 893-902. |
| [16] | 汪满金, 缪英杰, 汪胜利, 等. 胸肌变异伴腋静脉3支变异1例[J]. 中华解剖与临床杂志, 2022, 27(10): 729-730. |
| Wang M J, Miao Y J, Wang S L, et al. Pectoral muscle variation with 3 axillary vein variation: a case report[J]. Chinese Journal of Anatomy and Clinics, 2022, 27(10): 729-730. | |
| [17] | Loudon B L, Wong G R. Changing the view: preventing pneumothorax during transvenous pacemaker implantation[J]. J Cardiovasc Electrophysiol, 2024, 35(3): 438-439. |
| [18] | Morton M B, William J, Kistler P M, et al. Caudal fluoroscopic guidance for the insertion of transvenous pacing leads[J]. J Cardiovasc Electrophysiol, 2024, 35(3): 433-437. |
| [19] | Kaul R, Yang F, Shokr M, et al. Caudal tilt ultrasound-guided axillary venous access for transvenous pacing lead implant[J]. Heart Rhythm, 2024, 21(5): 662-667. |
| [20] | Deepti S, Singh D, Ghati N, et al. Utility of caudal angulation for venous access under fluoroscopic guidance during cardiovascular implantable electronic device implantation[J]. Cardiology, 2021, 146(4): 464-468. |
| [21] | Kim K H, Park K M, Nam G B, et al. Comparison of the axillary venous approach and subclavian venous approach for efficacy of permanent pacemaker implantation. 8-Year follow-up results[J]. Circ J, 2014, 78(4): 865-871. |
| [22] | Tagliari A P, Kochi A N, Saadi R P, et al. Insights from the axillary vein puncture guided by ultrasound versus cephalic vein dissection trial[J]. Future Cardiol, 2021, 17(6): 923-929. |
| [23] | Perna F, Flore F, Telesca A, et al. Ultrasound-guided axillary vein puncture versus landmark-guided approach for cardiac implantable electronic device placement[J]. Pacing Clin Electrophysiol, 2025, 48(1): 9-20. |
| [24] | Charles P, Ditac G, Montoy M, et al. Intra-pocket ultrasound-guided axillary vein puncture vs. cephalic vein cutdown for cardiac electronic device implantation: the ACCESS trial[J]. Eur Heart J, 2023, 44(46): 4847-4858. |
| [25] | Vitali F, Zuin M, Charles P, et al. Ultrasound-guided vs. fluoro-guided axillary venous access for cardiac implantable electronic devices: a patient-based meta-analysis[J]. Europace, 2024, 26(11): euae274. |
| [26] | Davis L, Chik W, Kumar S, et al. Axillary vein access using ultrasound guidance, venography or cephalic cutdown: what is the optimal access technique for insertion of pacing leads [J]. J Arrhythmia, 2021, 37(6): 1506-1511. |
| [27] | Mian M, Khan H R. Ultrasound utilization for implantation of cardiac implantable electronic devices[J]. Wien Klin Wochenschr, 2023, 135(23/24): 712-718. |
| [28] | Vitali F, Malagù M, Bianchi N, et al. Ultrasound-guided venous axillary access versus standard fluoroscopic technique for cardiac lead implantation: ZEROFLUOROAXI randomized trial[J]. JACC Clin Electrophysiol, 2024, 10(3): 554-565. |
| [29] | Sassone B, Simeti G, Virzì S, et al. The use of a handheld ultrasound device to guide the axillary vein access during pacemaker and cardioverter-defibrillator implantation. A feasibility study[J]. Rev Cardiovasc Med, 2022, 23(8): 258. |
| [30] | Silver E S, Nash M C, Liberman L. Implantation of permanent pacemaker and ICD leads in children using a three-dimensional electroanatomic mapping system as an aid to fluoroscopy[J]. Pacing Clin Electrophysiol, 2015, 38(4): 448-454. |
| [31] | Patel H, Hiner E, Naqvi A, et al. The safety and efficacy of electroanatomical mapping (EAM)-guided device implantation[J]. Pacing Clin Electrophysiol, 2019, 42(7): 897-903. |
| [32] | Ge X Z, Chen M N, Sha Z X, et al. Three-dimensional mapping in cardiac implantable electronic device: a feasible and effective alternative to fluoroscopy[J]. J Interv Card Electrophysiol, 2023, 66(3): 783-792. |
| [33] | Tagliari A P, Kochi A N, Mastella B, et al. Axillary vein puncture guided by ultrasound vs cephalic vein dissection in pacemaker and defibrillator implant: a multicenter randomized clinical trial[J]. Heart Rhythm, 2020, 17(9): 1554-1560. |
| [34] | Al-Sadawi M, Budzikowski A S. Unusual venous access for device implantation[J]. Am J Case Rep, 2019, 20: 1482-1486. |
| [35] | Griffiths S, Behar J M, Kramer D B, et al. The long-term outcomes of cardiac implantable electronic devices implanted via the femoral route[J]. Pacing Clin Electrophysiol, 2022, 45(4): 481-490. |
| [36] | 中国医师协会心律学专业委员会, 中华医学会心电生理和起搏分会. 无导线起搏器临床应用中国专家共识(2022)[J]. 中华心律失常学杂志, 2022, 26(3): 263-271. |
| Chinese Society of Arrhythmias, Chinese Society of Pacing and Electrophysiology. Chinese expert consensus on leadless pacemaker (2022)[J]. Chinese Journal of Cardiac Arrhythmias, 2022, 26(3): 263-271. | |
| [37] | 中国医师协会心律学专业委员会, 中华医学会心电生理和起搏分会. 无导线起搏器植入术操作流程及规范[J]. 中华心律失常学杂志, 2022, 26(4): 318-324. |
| Chinese Society of Arrhythmias, Chinese Society of Pacing and Electrophysiology. Leadless pacemaker: operation procedure and standard[J]. Chinese Journal of Cardiac Arrhythmias, 2022, 26(4): 318-324. | |
| [38] | 王天琦, 蓝荣芳, 吴翔, 等. 无导线起搏器的并发症[J]. 中华心律失常学杂志, 2024, 28(5): 393-395. |
| Wang T Q, Lan R F, Wu X, et al. Complications of leadless pacemaker[J]. Chinese Journal of Cardiac Arrhythmias, 2024, 28(5): 393-395. |
| [1] | 朱乃锋,张云龙,陈云丰. 喙锁韧带重建的解剖学研究和临床意义[J]. 上海交通大学学报(医学版), 2016, 36(3): 455-. |
| [2] | 仇晓霞, 程杰军. 一例PICC导管断裂后进入肺动脉的急救处理[J]. , 2013, 33(5): 600-. |
| 阅读次数 | ||||||
|
全文 |
|
|||||
|
摘要 |
|
|||||
