


氮氧化物是交通尾气和燃烧排放的主要成分。除直接危害外,它们还是大气光化学反应的关键前体,可通过形成二次气溶胶间接增加细颗粒物负荷,进而对人群健康产生复合影响。大量生成的有机颗粒物、硝酸盐和硫酸盐,正是可吸入颗粒物(particulate matter 10,PM10)和PM2.5的重要组分。在各类氮氧化物中,NO2对人体健康的影响备受关注,已成为最危险的空气污染物之一[1]。目前相关研究表明,NO2的短期或长期暴露,均与心血管疾病(cardiovascular disease,CVD)如中风和缺血性心脏病的发病率和死亡率的上升相关[2],但不同研究在暴露时间窗及敏感人群的识别上存在差异。一般认为,NO2短期暴露对心血管事件的触发效应,涉及快速的炎症与氧化应激反应、凝血通路激活与自主神经功能改变,而长期暴露则更多与动脉粥样硬化进展及代谢紊乱相关[3-4]。
血管内皮功能障碍(vascular endothelial dysfunction,VED)被视作CVD的早期标志与关键环节。从生物学机制而言,NO2可通过多种途径损伤内皮功能:其一,直接或间接诱导氧化应激,降低一氧化氮(nitric oxide,NO)的生物利用度(例如超氧阴离子与NO反应生成过氧亚硝酸盐)[5];其二,激活内皮细胞与免疫细胞,促使炎症因子[如白细胞介素-6(interleukin-6,IL-6)、肿瘤坏死因子-α(tumor necrosis factor-α,TNF-α)]、黏附分子[如细胞间黏附分子-1(intercellular adhesion molecule-1,ICAM-1)、血管细胞黏附分子-1(vascular cell adhesion molecule-1,VCAM-1)]上调,进而促进白细胞与内皮的黏附以及微血管炎症反应[6];其三,通过影响血小板活化和血栓前状态改变血流动力学[7]。老年人常患多种慢性疾病,如高血压、糖尿病、高脂血症等,这些危险因素会加剧内皮细胞功能障碍,致使老年人对空气污染的健康影响更为敏感,故而VED在老年人中更为普遍。有研究[8]表明,人群在短期NO₂暴露下,全因死亡风险显著升高。基于此背景,深入研究NO2暴露时间与浓度对中国老年人内皮功能的影响显得尤为迫切。
血流介导的血管舒张功能(flow-mediated dilation,FMD)检测是一种经典的无创超声检测血管内皮功能的方法[9-10]。通过FMD早期发现内皮功能障碍,有助于积极有效地开展动脉粥样硬化性心血管疾病(atherosclerotic cardiovascular disease,ASCVD)的一级预防工作。本研究以65岁及以上老年人为研究对象,运用FMD技术评估血管内皮功能,并采用分布式滞后非线性模型(distributed lag non-linear model,DLNM)分析NO2短期暴露时间与浓度对FMD和VED的独立效应,旨在弥补现有研究在老年人群内皮功能敏感性及暴露时序性识别方面的不足,为完善老年人群空气污染一级预防体系提供证据支持。
1 对象与方法
1.1 研究对象
本研究为横断面研究,共纳入812名65岁及以上的老年受试者,这些受试者均于2020—2022年间在上海交通大学医学院附属同仁医院心血管内科接受了FMD检测。受试者的排除标准包括:①年龄小于65岁。②居住地不在上海市范围内。③临床数据不完整。依据临床常用阈值,以FMD 6%为分界进行分组:FMD<6%定义为VED组,FMD≥6%为非VED组。
1.2 污染暴露评估
基于受试者居住地址的污染数据,我们估算了受试者的NO₂暴露水平。空气污染数据来源于中国空气污染追踪(Tracking Air Pollution in China,TAP)平台(
1.3 FMD检测
检测时,受试者取仰卧位,手臂固定于探头下方的专用支架上,使用血压计袖带加压于上臂,在肱动脉处诱发短暂缺血。血管内皮通常会对缺血刺激产生反应,通过释放NO引发血管扩张;采用10 MHz线性超声探头(UNEXEF18VG,UNEX株式会社,日本)检测这一变化。检测数据通过计算机辅助分析系统(UNEXEF18VG,名古屋Unex公司,日本)进行处理。所有检测操作均由经过专业认证的护理人员执行并监督。
1.4 统计学分析
采用DLNM评估NO₂短期暴露对FMD的长期影响。首先利用广义线性模型(generalized linear model,GLM)拟合DLNM,采用三自由度的自然立方样条函数,计算不同lag day的NO₂浓度每分位数增加所对应的FMD百分比变化[12]。根据既往研究[13-14]显示的污染物暴露后10 d内影响最为显著,故选择Lag0~Lag10作为观察窗口。GLM采用逐步调整策略:模型1未调整任何协变量;模型2调整了年龄+性别+吸烟+饮酒+季节(代表气象因素);模型3进一步调整疾病状态[CVD家族史+高血压+糖尿病+血脂异常+冠状动脉疾病(coronary artery disease,CAD)]。在确定各lag day的重要组分后,利用基线值进行分层分析以识别潜在危险因素和易感人群。
所有统计分析均采用RStudio(4.1.2版)软件完成。符合正态分布的定量数据用x±s表示,不符合正态分布的定量数据用M(Q1,Q3)表示;定性数据用n(%)表示。P<0.05表示差异具有统计学意义。
2 结果
2.1 基线特征分析
表1 受试者基线特征
Tab 1
| Population characteristic | Overall (n=812) | Non-VED (n=178) | VED (n=634) | P value |
|---|---|---|---|---|
| FMD/% | 4.20 (2.80, 5.62) | 7.30 (6.53, 8.47) | 3.60 (2.40, 4.60) | <0.001 |
| Age/year | 70.61±5.43 | 71.08±5.68 | 68.94±4.03 | <0.001 |
| Gender/n(%) | <0.001 | |||
| Female | 495 (61.0) | 131 (73.6) | 364 (57.4) | |
| Male | 317 (39.0) | 47 (26.4) | 270 (42.6) | |
| Smoking/n(%) | 0.041 | |||
| No | 704 (86.7) | 163 (91.6) | 541 (85.3) | |
| Yes | 108 (13.3) | 15 ( 8.4) | 93 (14.7) | |
| Drinking/n(%) | 0.119 | |||
| No | 714 (87.9) | 163 (91.6) | 551 (86.9) | |
| Yes | 98 (12.1) | 15 ( 8.4) | 83 (13.1) | |
| Hypertension/n(%) | 0.157 | |||
| No | 117 (14.4) | 32 (18.0) | 85 (13.4) | |
| Yes | 695 (85.6) | 146 (82.0) | 549 (86.6) | |
| Diabetes/n(%) | 0.481 | |||
| No | 658 (81.0) | 148 (83.1) | 510 (80.4) | |
| Yes | 154 (19.0) | 30 (16.9) | 124 (19.6) | |
| Dyslipidemia/n(%) | 0.189 | |||
| No | 448 (55.2) | 90 (50.6) | 358 (56.5) | |
| Yes | 364 (44.8) | 88 (49.4) | 276 (43.5) | |
| CAD/n(%) | 0.357 | |||
| No | 736 (90.6) | 165 (92.7) | 571 (90.1) | |
| Yes | 76 ( 9.4) | 13 ( 7.3) | 63 ( 9.9) | |
| CVD/n(%) | 0.490 | |||
| No | 790 (97.3) | 175 (98.3) | 615 (97.0) | |
| Yes | 22 ( 2.7) | 3 (1.7) | 19 ( 3.0) | |
| CVD family history/n(%) | 1.000 | |||
| No | 652 (80.3) | 143 (80.3) | 509 (80.3) | |
| Yes | 160 (19.7) | 35 (19.7) | 125 (19.7) | |
| Season/n(%) | 0.178 | |||
| Spring | 190 (23.4) | 41 (23.0) | 149 (23.5) | |
| Summer | 229 (28.2) | 59 (33.1) | 170 (26.8) | |
| Autumn | 133 (16.4) | 21 (11.8) | 112 (17.7) | |
| Winter | 260 (32.0) | 57 (32.0) | 203 (32.0) |
图1
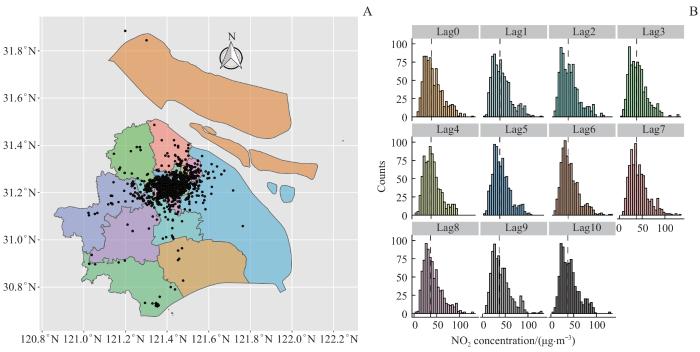
图1
受试者的空间分布与NO2 浓度水平
Note: A. Geographic distribution of the study participants in Shanghai. B. Ambient NO2 concentrations (μg·m-3) from lag 0 to lag 10 days.
Fig 1
Geographical distribution of the study participants and ambient NO2 concentration levels
研究结果显示,NO2浓度每增加1个分位数,Lag0、Lag1、Lag2和Lag5均观察到FMD显著降低,lag0、lag5和lag6时VED风险的显著增加(表2)。
表2 FMD百分比变化与VED风险分析
Tab 2
| Item | Model 1 | P value | Model 2 | P value | Model 3 | P value |
|---|---|---|---|---|---|---|
| FMD | ||||||
| Lag0/% | -18.00 (-32.56, -3.44) | 0.015 | -20.99 (-38.71, -3.27) | 0.020 | -21.40 (-39.13, -3.67) | 0.018 |
| Lag1/% | -19.49 (-34.03, -4.95) | 0.009 | -26.40 (-43.83, -8.96) | 0.003 | -26.87 (-44.34, -9.40) | 0.003 |
| Lag2/% | -14.86 (-29.48, -0.24) | 0.046 | -18.78 (-36.85, -0.71) | 0.042 | -19.53 (-37.62, -1.44) | 0.034 |
| Lag3/% | -12.30 (-26.99, 2.39) | 0.101 | -17.20 (-35.56, 1.16) | 0.066 | -18.14 (-36.52, 0.24) | 0.053 |
| Lag4/% | -8.86 (-23.81, 6.08) | 0.245 | -14.18 (-32.17, 3.81) | 0.122 | -15.05 (-33.10, 3.00) | 0.102 |
| Lag5/% | -15.87 (-30.63, -1.12) | 0.035 | -18.49 (-35.28, -1.69) | 0.031 | -19.64 (-36.48, -2.81) | 0.022 |
| Lag6/% | -12.94 (-27.78, 1.90) | 0.087 | -14.82 (-32.36, 2.72) | 0.098 | -15.93 (-33.49, 1.63) | 0.075 |
| Lag7/% | -9.43 (-24.09, 5.24) | 0.208 | -10.54 (-27.70, 6.62) | 0.229 | -11.96 (-29.14, 5.23) | 0.173 |
| Lag8/% | -11.50 (-26.28, 3.27) | 0.127 | -12.08 (-28.82, 4.66) | 0.157 | -13.48 (-30.21, 3.25) | 0.114 |
| Lag9/% | -8.13 (-22.77, 6.50) | 0.276 | -6.73 (-23.45, 9.99) | 0.430 | -8.07 (-24.82, 8.67) | 0.345 |
| Lag10/% | -6.19 (-20.77, 8.39) | 0.405 | -6.53 (-23.36, 10.30) | 0.447 | -7.55 (-24.44, 9.34) | 0.381 |
| VED | ||||||
| Lag0 | 1.21 (1.04, 1.41) | 0.014 | 1.26 (1.04, 1.53) | 0.019 | 1.27 (1.05, 1.55) | 0.016 |
| Lag1 | 1.13 (0.97, 1.31) | 0.111 | 1.17 (0.97, 1.42) | 0.106 | 1.18 (0.98, 1.44) | 0.092 |
| Lag2 | 1.11 (0.96, 1.29) | 0.166 | 1.14 (0.94, 1.39) | 0.189 | 1.15 (0.94, 1.40) | 0.169 |
| Lag3 | 1.12 (0.97, 1.31) | 0.139 | 1.17 (0.96, 1.43) | 0.122 | 1.18 (0.97, 1.45) | 0.107 |
| Lag4 | 1.06 (0.91, 1.23) | 0.448 | 1.10 (0.90, 1.33) | 0.339 | 1.11 (0.91, 1.35) | 0.300 |
| Lag5 | 1.20 (1.03, 1.40) | 0.020 | 1.26 (1.04, 1.51) | 0.015 | 1.27 (1.05, 1.53) | 0.013 |
| Lag6 | 1.16 (0.99, 1.35) | 0.061 | 1.20 (0.99, 1.46) | 0.066 | 1.22 (1.01, 1.49) | 0.045 |
| Lag7 | 1.04 (0.90, 1.21) | 0.603 | 1.03 (0.85, 1.24) | 0.759 | 1.04 (0.86, 1.26) | 0.687 |
| Lag8 | 1.14 (0.98, 1.33) | 0.093 | 1.18 (0.98, 1.41) | 0.075 | 1.19 (0.99, 1.43) | 0.064 |
| Lag9 | 1.07 (0.92, 1.24) | 0.374 | 1.05 (0.88, 1.26) | 0.594 | 1.06 (0.88, 1.27) | 0.534 |
| Lag10 | 1.03 (0.88, 1.19) | 0.701 | 1.02 (0.85, 1.22) | 0.830 | 1.03 (0.85, 1.24) | 0.759 |
2.2 NO₂对FMD和VED的联合效应分析
调整了前述所有协变量后,这种显著性依然存在(Lag0:-21.40%,95%CI -39.13%~-3.67%;Lag1:-26.87%,95%CI -44.34%~-9.40%;Lag2:-19.53%,95%CI -37.62%~-1.44%;Lag5:-19.64%,95%CI -36.48%~-2.81%)。FMD的变化与Lag0、Lag1、Lag2和Lag5的暴露显著相关。为探究不同NO2浓度水平对FMD的潜在影响,我们固定了Lag4、Lag5和Lag6这3个时间点进行分析(图2A)。同时,以NO2浓度中位数为参照,通过固定特定浓度水平(35、60和85 μg/m³),评估了NO2对FMD的延迟效应(图2B)。在模型中,NO2暴露对FMD的影响呈现明显的时间依赖性趋势:在Lag0时即出现轻度下降,至Lag1和Lag5时效应最为显著,FMD平均下降幅度分别为0.12%(95%CI -0.20%~-0.04%)和0.18%(95%CI -0.26%~-0.09%)。当滞后时间超过7 d后,该效应逐渐减弱并趋于稳定。整体趋势显示,短期NO2暴露(1~5 d)与FMD呈负向关联,表明NO2可在暴露后数日内诱发可测的内皮舒张功能损害。
图2
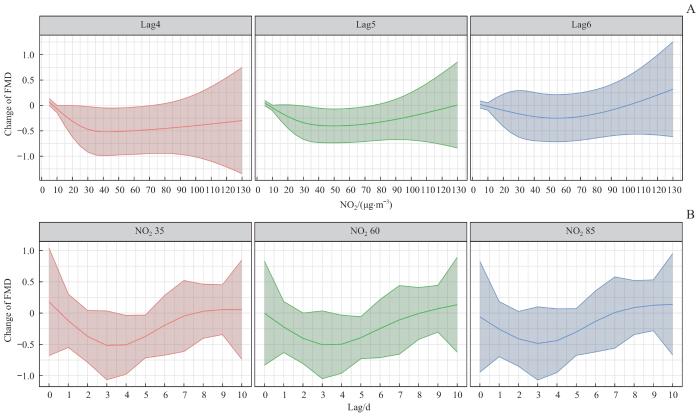
图2
固定NO2 浓度与固定滞后天数对FMD的影响关系
Note: A. The impact of NO2 exposure on FMD in Lag4, Lag5, and Lag6. B. Impact of fixed levels of NO2 (35, 60, and 85 μg/m3) on FMD from Lag0 to Lag10.
Fig 2
Correlation between fixed NO₂ levels and fixed lag days on FMD
在调整所有既定协变量后,NO2暴露与VED风险的显著性关联仍然存在(Lag0:OR=1.27,95%CI 1.05~1.55;Lag5:OR=1.27,95%CI 1.05~1.53;Lag6:OR=1.22,95%CI 1.01~1.49)。鉴于VED风险在Lag5表现出最显著的统计学意义,我们通过固定Lag4、Lag5和Lag6这3个时间点,系统分析了不同NO2暴露水平对VED的影响程度(图3A)。结果显示NO2浓度与VED风险的滞后效应呈现近似的“延迟峰值”特征。在Lag0~Lag2阶段,风险略有上升,随后逐步回落至基线水平。这一趋势提示NO2暴露对血管内皮功能障碍的作用具有累积性和滞后性,暴露后4~6 d为效应最强的时间窗。进一步分析显示,当NO2浓度固定在第75百分位水平(约80 μg/m3)时,FMD与VED的反应幅度分别较第25百分位(约30 μg/m3)显著变化(P<0.01),强化了浓度-反应关系的稳健性。为进一步阐明NO2暴露的延迟效应,研究选取特定浓度水平(40、60和80 μg/m3),以中位数值作为参照基准,评估了NO2对VED的时序性影响(图3B)。
图3
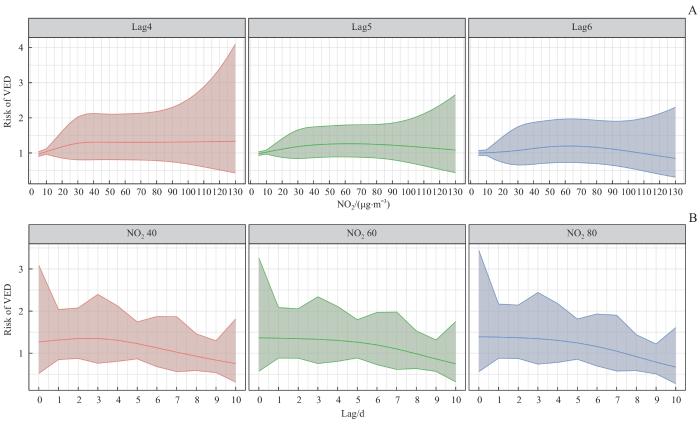
图3
固定NO2 浓度与特定滞后天数对VED的关联性分析
Note: A. Varying effects of NO2 exposure on VED at Lags 4, 5, and 6. B. Impacts of fixed NO2 concentrations (40, 60, and 80 μg/m3) on VED from Lag0 to Lag10.
Fig 3
Association between fixed NO2 levels and fixed lag days on VED
图4
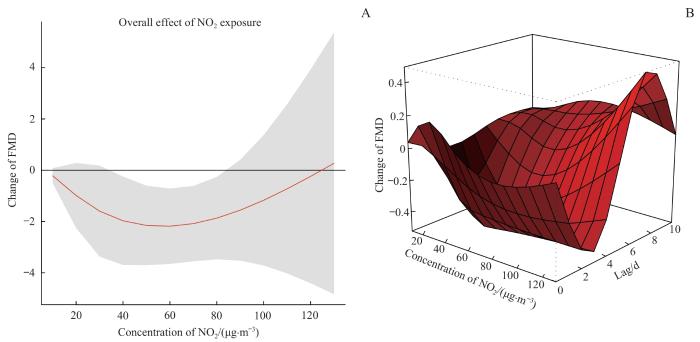
图4
NO2 短期暴露对FMD影响的累积效应及三维模型
Note: A. Cumulative impact of brief exposure to NO2 on FMD. B. Overview of the correlation between NO2 concentration and FMD shifts from Lag0 to Lag10, as provided by the 3D model.
Fig 4
3D model and cumulative impact of short-term NO2 exposure on FMD
2.3 亚组分析结果
基于Lag5的亚组分析显示了FMD的累积差异(图5A)。研究发现某些人群对NO2短期暴露更为敏感,其中有CAD病史者的FMD下降程度较无CAD病史者更为显著(交互作用P=0.007)。
图5
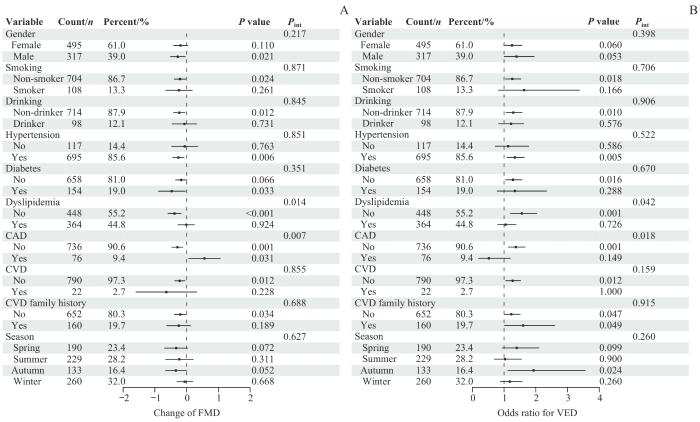
图5
亚组分析结果
Note: A. Subgroup analysis of NO2 at Lag5 and FMD. B. Subgroup analysis of NO2 at Lag5 and risk of VED. int—interaction.
Fig 5
Subgroup analysis results
通过Lag5亚组分析还发现不同亚组具有不同的VED累积风险(图5B)。研究证实部分人群在NO2短期暴露中风险更高,但有CAD病史者的VED风险反而低于无CAD病史者(交互作用P=0.018)。
此外,血脂异常分层的交互作用检验亦提示上述效应存在差异(交互作用P=0.014,交互作用P=0.042)。
3 讨论
众所周知,世界卫生组织空气质量指南[1]规定的NO2 AQG推荐值为25 μg/m³,而中国《环境空气质量标准》[17]规定的24 h平均NO₂一级标准限值为80 μg/m³。本研究在812名≥65岁的老年人中发现,NO2短期暴露与FMD水平呈显著负相关,尤其在Lag0、Lag1、Lag2和Lag5时效下表现最为明显;同时,在各滞后时间中,VED风险于lag5表现出最为显著的升高趋势。累积暴露分析进一步显示,当NO2浓度处于35~85 μg/m³范围内时,FMD呈浓度依赖性下降趋势;并且在调整年龄、性别、吸烟、饮酒及基础疾病等多种协变量后,该结果依然稳健,提示NO₂短期暴露对老年人群内皮功能具有独立不良影响,也为中国改善老年人空气污染一级预防的标准提供了思路。亚组分析发现,无高脂血症或无CAD史的受试者更易受到短期NO2暴露的影响,提示该类老年群体在短期暴露下一级预防的指导意义更明确。
与既有研究[18]相比,本研究的发现与多项关于NO2与心血管结局的流行病学报告相一致,但通过FMD这一早期功能学指标,更加明确了NO2的短期浓度-时间效应特征,提示应更加重视空气污染的一级预防。既往多数研究以死亡或住院事件为终点,难以揭示短期暴露的生理学变化。本研究通过连续lag day的暴露分析,发现内皮功能的下降可在数日内出现,与空气污染诱导的炎性反应、氧化应激及血液动力学改变的时程相符[19-21]。值得注意的是,Lag5的延迟效应提示NO2相关损伤可能具有一定累积性:暴露后数小时内氧化应激反应被激活,随后炎症介质释放、内皮黏附分子上调及血小板聚集等过程在3~7 d内逐渐放大,最终导致FMD显著下降、VED风险升高。这与实验研究中NO2暴露后炎症细胞浸润及微血管功能损伤的时间特征一致[6]。
亚组分析中,冠心病患者的VED风险低于非冠心病患者的结果表面上与预期不符,最可能的解释为药物缓冲效应:CAD患者多长期使用他汀类、血管紧张素转换酶抑制剂/血管紧张素Ⅱ受体拮抗剂(angiotensin-converting enzyme inhibitor/angiotensin Ⅱ receptor blocker,ACEI/ARB)及抗血小板药物;这些药物可减轻氧化应激及炎性反应,从而削弱NO2的急性危害。未来分析可在模型中引入用药信息,并对FMD基线值进行连续校正,以验证交互项的统计显著性。
本研究的另一局限在于仅考虑了NO2单污染物暴露。考虑到实际环境中多污染物共存,NO2可能与PM2.5或O3等污染物存在协同或交互效应[7]。若数据允许,可在后续分析中引入双污染物模型,以识别 NO2独立效应及共暴露影响。另一方面,尽管控制了多项协变量,但潜在的残余混杂仍无法完全排除,如受试者的饮食习惯、体力活动或社会经济因素等。
未来研究方向包括:开展多城市面板队列研究,验证暴露-反应关系及时间效应外推性;结合生化与分子指标,探索NO2诱导内皮功能损伤的分子机制,如内皮型NO合酶(endothelial nitric oxide synthase,eNOS)活性、NADPH氧化酶表达与炎症信号通路;构建暴露‒生物标志物‒功能损害的“时序链条”,以完善污染‒健康影响的生理学解释。
NO₂短期暴露对老年人(≥65岁)血管内皮功能具有显著负面影响,且该影响存在4~6 d的延迟效应。值得注意的是,NO2与FMD降低和VED风险增加显著相关,暴露后第5天的影响最为显著。无冠心病和无高脂血症病史的患者对高浓度NO2暴露的不良影响表现出更强的易感性。老年人作为易感人群,对空气污染物具有更高的敏感性,这种易感性使得该群体面临更大的环境健康风险。更广泛的人群研究和更深的机制研究值得未来进一步推进,以减少NO2的不利影响并为未来预防相关疾病的潜在发生和死亡做出科学指导及理论支撑。
伦理批准和知情同意
所有采用的方法均符合1975年《赫尔辛基宣言》及其2008年修订版,并遵循相关(国家及机构)人体实验伦理委员会的伦理指南。本研究方案经上海交通大学医学院附属同仁医院伦理委员会审批通过(批件号:K2023-021-01)。所有受试者在研究开始前均签署了知情同意书。
Ethics Approval and Patient Consent
All methods used were compliant with the Declaration of Helsinki of 1975, as amended in 2008, and with the ethical guidelines of the relevant committees on human experimentation (national and institutional). All participants provided their informed consent to participate in the research. This study protocol was approved by the Ethics Committee of Tongren Hospital, Shanghai Jiao Tong University School of Medicine (Approval No. K2023-021-01). All participants provided written informed consent prior to the commencement of the study.
作者贡献
姜绮霞负责研究设计与课题构思。钟林杉和丁琳负责数据采集;钟林杉制定分析方案、完成统计分析并负责论文撰写与修改。所有作者均阅读并同意了最终稿件的提交。
Authors' Contributions
JIANG Qixia made substantial contributions to the conception of the study. ZHONG Linshan and DING Lin acquired the data. ZHONG Linshan defined the analytical strategy, conducted the statistical analysis, and drafted the manuscript. All authors have read the final version of the paper and consented to its submission.
利益冲突声明
所有作者声明不存在利益冲突。
Conflict of Interests
All authors declare no relevant conflict of interests.
参考文献


